
 comparison
Why Vitamin B12 Injections Are Better: Absorption Guide
Table of Contents
- How B12 Injections Bypass Digestion Entirely
- B12 Injection Absorption Rate vs Oral Supplements
- Who Actually Needs Injections: Deficiency, Diet, and Age
- B12 Injection Frequency for Deficiency and Maintenance
- How to Administer B12 Injections Safely at Home
- B12 Injection Side Effects and Risks You Should Know
- Long-Term Monitoring and What Blood Tests to Track
- Frequently Asked Questions
Last Updated: September 16, 2026
How B12 Injections Bypass Digestion Entirely
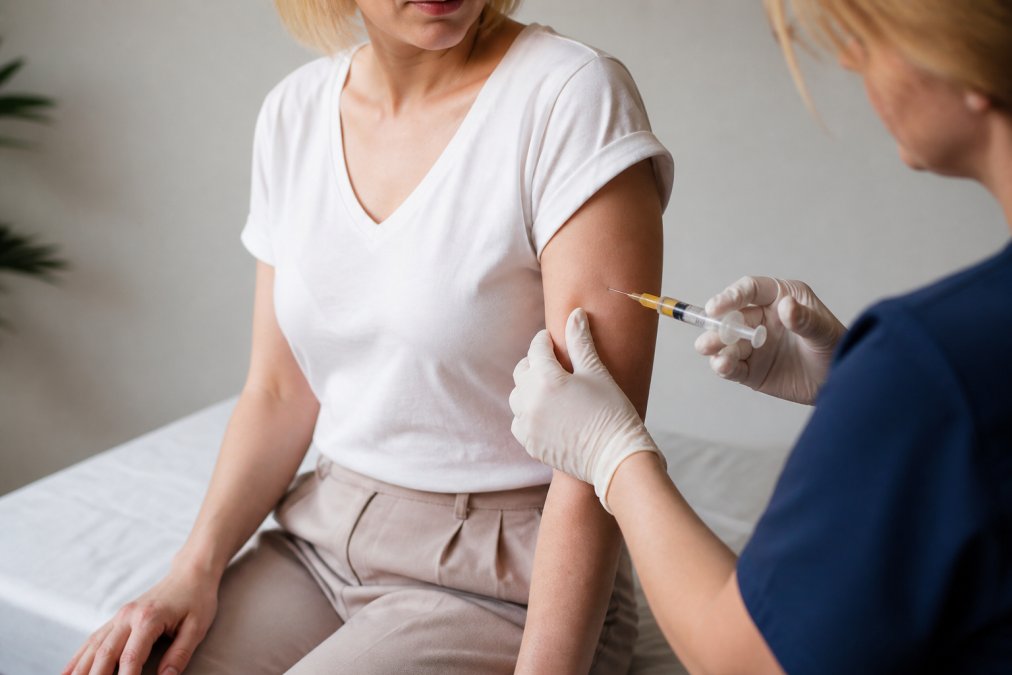
Vitamin B12 injections deliver cobalamin straight into muscle tissue, skipping the digestive process that often fails people with absorption problems. This is the core reason why vitamin B12 injections are better for anyone whose gut cannot reliably pull B12 from food or pills.
B12 Injection Absorption Rate vs Oral Supplements
The B12 injection absorption rate approaches 100% for intramuscular delivery, while oral supplements typically deliver only a small fraction of their stated dose. That gap explains why injections remain the clinical standard for confirmed deficiency.
| Delivery Method | Absorption | Best For | Key Limitation |
|---|---|---|---|
| Intramuscular injection | Near complete | Malabsorption, pernicious anemia | Requires needle and technique |
| Sublingual tablets | Moderate | Mild dietary shortfalls | Still needs some gut function |
| Oral tablets | Low to moderate | Vegans with healthy guts | Intrinsic factor dependent |
The Math Behind 100% Bioavailability
Bioavailability is the share of a dose that actually reaches your bloodstream. For an intramuscular injection, that share is essentially the full dose, because the muscle tissue releases cobalamin directly into circulation. Oral bioavailability drops sharply as the dose rises, since absorption pathways saturate. This is why a high-dose oral tablet does not equal an injection, even when the label numbers look similar.
Who Actually Needs Injections: Deficiency, Diet, and Age
People with diagnosed deficiency, malabsorption conditions, or restricted diets benefit most from injections. Pernicious anemia, gastrointestinal surgery, and certain medications that suppress stomach acid all interfere with B12 uptake. Older adults often produce less intrinsic factor, which reduces gastrointestinal absorption over time.

Vegan and Vegetarian Protocols
Plant foods do not contain meaningful B12, so vegans and vegetarians rely on fortified foods or supplements. A common mistake is assuming a multivitamin covers it. Many people on plant-based diets find that periodic injections provide more consistent serum vitamin B12 levels than daily tablets, especially when dietary intake is inconsistent.
B12 Injection Frequency for Deficiency and Maintenance
B12 injection frequency for deficiency follows a two-phase pattern: a loading phase to rebuild depleted stores, then a maintenance phase to hold serum levels steady. The exact numbers depend on your diagnosis, but the structure is consistent enough to plan around.
Loading Phase
For confirmed deficiency, a typical clinical approach is a series of injections given more frequently at the start, often every other day or a few times per week for the first one to two weeks, followed by weekly injections for roughly a month. The goal is to saturate liver stores, which can hold a substantial reserve of cobalamin.
Maintenance Phase
Once serum levels normalize and symptoms resolve, most clinicians step down to monthly injections. Some patients, particularly those with pernicious anemia or after gastric bypass, stay on monthly dosing indefinitely. Others with milder absorption issues may stretch to every two or three months if bloodwork supports it. A common pattern is monthly for the first year, then reassessment.
What Actually Drives the Schedule
Three variables move the interval:
- The underlying cause. Pernicious anemia and ileal resection typically require lifelong monthly dosing. Dietary shortfalls in vegans often need less.
- Serum B12 and methylmalonic acid results. These are the objective markers. Symptoms alone are unreliable because fatigue and brain fog have many causes.
- Age and medication load. Long-term use of proton pump inhibitors or metformin can reduce absorption and push the interval shorter.
A Concrete Monitoring Cadence
A reasonable schedule most practitioners find workable:
- Baseline serum B12, methylmalonic acid, and homocysteine before starting.
- Retest roughly 4 to 8 weeks after the loading phase begins.
- Retest every 3 to 6 months during the first year of maintenance.
- Move to annual testing once levels are stable and symptoms are gone.
If methylmalonic acid stays elevated despite a normal serum B12, that signals functional deficiency and usually means the interval is too long or the dose is too low.
Why This Matters More Than the 'Feel' Test
Many people judge their schedule by how they feel on injection day. That is a poor proxy. Serum markers catch drift weeks before symptoms return, and they prevent the opposite error, injecting more often than needed because of a placebo lift. The schedule should follow the labs, not the calendar and not the mood.
How to Administer B12 Injections Safely at Home
Learning how to administer B12 injections safely at home comes down to sterile technique and consistency. Many people self-inject after training, which makes a reliable supply of vials and needles essential.
Step-by-Step Injection Technique
- Wash your hands thoroughly and gather supplies: vial, syringe, alcohol swabs, and a sharps container.
- Wipe the vial top and the injection site with separate alcohol swabs.
- Draw the dose, tap out air bubbles, and confirm the volume.
- Insert the needle into the muscle at a 90-degree angle.
- Inject slowly, withdraw, and dispose of the needle in the sharps container.
A common mistake is reusing needles or skipping site rotation. Both raise the risk of adverse reactions and infection.
B12 Injection Side Effects and Risks You Should Know
B12 injection side effects are usually mild and short-lived, but the bigger risk in the consumer market is not the needle, it is unnecessary treatment driven by wellness marketing. Here is what the evidence actually supports.
Common, Expected Reactions
- Injection-site soreness, redness, or a small bruise, the most frequent complaint.
- Brief swelling or a warm sensation at the site.
- A temporary flush or feeling of warmth in the minutes after the shot.
- Mild diarrhea or nausea in some people, particularly at higher doses.
These typically resolve within a day or two and do not require intervention beyond a cold compress and site rotation.
Rare but Real Risks
- Allergic reaction. True anaphylaxis to cyanocobalamin or hydroxocobalamin is rare but documented (pubmed.ncbi.nlm.nih.gov). Anyone with a history of reactions to injectable vitamins should be dosed in a clinical setting first.
- Infection from poor technique. Reusing needles, skipping alcohol swabs, or injecting through dirty skin raises the risk of cellulitis or abscess.
- Nerve or vessel injury. Improper landmarking for gluteal injections can hit the sciatic nerve. This is why training matters before self-administering.
- Cobalt sensitivity. A small subset of people react to the cobalt core of the cobalamin molecule, presenting as a rash or itching.
The Claims That Do Not Hold Up
Two marketing claims deserve direct pushback:
Weight loss. There is no credible evidence that B12 injections cause weight loss in people who are not deficient. The shots are sometimes bundled into 'lipotropic' injections alongside methionine, inositol, and choline, and any weight change is attributed to the cocktail, not the B12. If you are not deficient, correcting B12 will not move the scale.
Toxicity and Why Monitoring Matters
B12 is water-soluble, so excess is generally excreted in urine, and true toxicity is rare. That does not make indefinite high-dose injection harmless or free. Unnecessary treatment carries cost, needle-stick risk, and the chance of masking another cause of your symptoms, thyroid disease, sleep apnea, iron deficiency, and depression all produce fatigue that B12 will not fix.
When to Stop or Pause
If follow-up labs stay normal for a year on maintenance dosing and the original cause has resolved (for example, a temporary dietary gap), it is reasonable to discuss stepping down or switching to oral supplementation with your clinician. Injections are the right tool for malabsorption, they are not a permanent upgrade for everyone.
Long-Term Monitoring and What Blood Tests to Track
Bioavailability nuances matter here too. Two people on the same dose can land at very different serum concentrations, so your results, not someone else's schedule, should drive adjustments.
Frequently Asked Questions
Is there any downside to getting B12 shots?
B12 injections are generally well-tolerated, but they can cause mild side effects like pain or redness at the injection site, headache, or nausea. Rarely, serious allergic reactions may occur. People with kidney disease or certain blood disorders should consult a doctor before starting. Long-term use without monitoring serum vitamin B12 levels can mask other conditions. For most people with a confirmed deficiency, the benefits outweigh the risks when used under proper guidance.
How do B12 injections compare to oral supplements for absorption?
Injections deliver cobalamin directly into muscle tissue, achieving nearly 100% bioavailability and raising serum vitamin B12 levels quickly. Oral supplements rely on gastrointestinal absorption, which is limited by intrinsic factor and can be as low as 1-2% for high doses. For people with malabsorption conditions like pernicious anemia or those who have had gastrointestinal surgery, injections bypass these barriers entirely. Even sublingual tablets may not match the absorption rate of an intramuscular injection.
Who is the ideal candidate for B12 injection therapy?
Ideal candidates include individuals with diagnosed B12 deficiency, especially those with malabsorption issues such as pernicious anemia, celiac disease, or Crohn's disease. Vegans and vegetarians who struggle to maintain adequate levels through diet or oral supplements may also benefit. Older adults with decreased stomach acid production and anyone who has had bariatric surgery often need injections. A blood test confirming low serum B12 is the first step before starting therapy.
What happens to your weight when you take B12?
B12 does not directly cause weight loss. However, correcting a deficiency can restore energy levels and improve metabolism, which may support weight management efforts indirectly. Some people report feeling more motivated to exercise and make healthier food choices once their fatigue lifts. That said, B12 injections are not a weight-loss treatment, and no clinical guidelines recommend them for that purpose. Focus on diet and activity for sustainable weight control.
Managing a B12 deficiency without a clear plan leaves you guessing about energy, focus, and long-term nerve health. Buy-Otc.com supplies discounted B12 shots, B1 and B6 injectables, vitamin C shots, and needles, all backed by Geotrust SSL protection and 5 star customer service. Registered users get access to ongoing discounts and special offers. Get started with Buy-Otc.com and build a reliable injection routine that keeps your levels where they belong.